Medical Insurance
Atlantic Packaging offers two medical plans administered through our Third-Party Administrator, Health Plans, Inc.
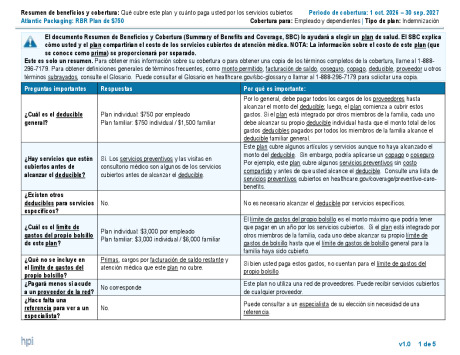
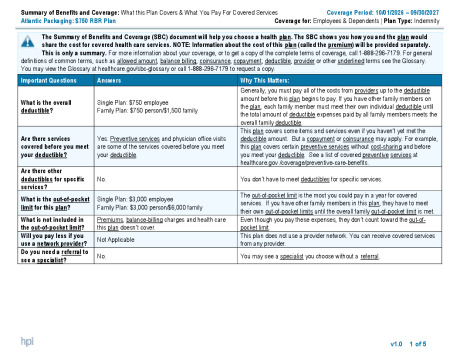
RBR Medical Plan
The RBR plan is administered by HPI and has no network. Preventive care is still covered at 100%, with no copay or out-of-pocket cost. Copays are:
- $25 for primary care visits
- $50 for specialist visits
- $250 for the first ER visit
The annual deductible is $750 per person, and the out-of-pocket maximum is $3,000 per person. That means after you pay the first $750 in covered expenses, you’ll pay 20% of the remaining costs until you hit the $3,000 cap. For families, two members must each meet the $750 deductible and $3,000 out-of-pocket max, totaling $1,500 deductible and $6,000 out-of-pocket max for the family.
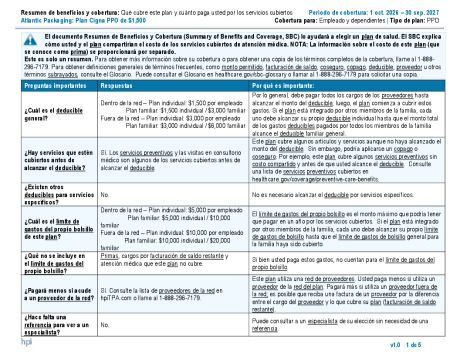
CIGNA Network Medical Plan
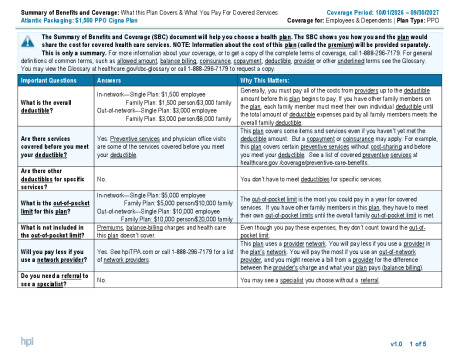
The Network plan, offered through HPI and using the CIGNA Network, gives you access to a broader range of providers and covers 98% of our geographic footprint but comes with higher costs due to fewer network discounts. Preventive care is still fully covered, but the rest of the costs are a bit different.
- $35 for primary care visits
- $75 for specialist visits
- $500 for the first ER visit
The annual deductible is $1,500 per person and $3,000 per family, with an out-of-pocket maximum of $5,000 per person and $10,000 per family. Just like the RBR plan, once you meet your deductible, you’ll pay 20% of covered expenses until you hit that out-of-pocket max.
The chart below provides a brief outline of what is offered.
Cost of Coverage
Employee Contributions
| Weekly Employee Contributions | ||||||||
|---|---|---|---|---|---|---|---|---|
| RBR Plan | Network Plan | |||||||
| Standard Rate | Wellness Rate* | Standard Rate | Wellness Rate* | |||||
| Employee | $46.77 | $21.51 | $46.77 | $21.51 | ||||
| Employee & Spouse | $133.18 | $91.89 | $133.18 | $91.89 | ||||
| Employee & Child(ren) | $102.02 | $67.34 | $102.02 | $67.34 | ||||
| Employee & Family | $240.32 | $182.64 | $240.32 | $182.64 | ||||
| Monthly Employee Contributions | ||||||||
| RBR Plan | Network Plan | |||||||
| Standard Rate | Wellness Rate* | Standard Rate | Wellness Rate* | |||||
| Employee | $206.56 | $95.02 | $206.56 | $95.02 | ||||
| Employee & Spouse | $588.21 | $405.87 | $588.21 | $405.87 | ||||
| Employee & Child(ren) | $450.59 | $297.40 | $450.59 | $297.40 | ||||
| Employee & Family | $1,061.41 | $806.67 | $1,061.41 | $806.67 | ||||
*Wellness premiums are based on program participation
Coverage
| Medical Plan Benefits | RBR Plan | Network Plan | ||
|---|---|---|---|---|
| Annual Deductible | In-Network | Out of Network | ||
| Individual | $750 | $1,500 | $3,000 | |
| Family | $1,500 | $3,000 | $6,000 | |
| Coinsurance | 20% | 20% | 40% | |
| Maximum Out-of-Pocket* | ||||
| Individual | $3,000 | $5,000 | $10,000 | |
| Family | $6,000 | $10,000 | $20,000 | |
| Physician Office Visit | ||||
| Primary Care | $25 copay | $35 copay | 40% after deductible | |
| Specialty Care | $50 copay | $75 copay | 40% after deductible | |
| Teladoc | $0 copay | $0 copay | Not Available | |
| Preventive Care | ||||
| Adult Periodic Exams | 100% Covered | 100% Covered | 40% after deductible | |
| Well-Child Care | 100% Covered | 100% Covered | 40% after deductible | |
| Diagnostic Services | ||||
| X-ray and Lab Tests | 100% Covered | 100% Covered | 40% after deductible | |
| Complex Radiology | 20% after deductible | 20% after deductible | 40% after deductible | |
| Urgent Care Facility | $50 copay | $100 copay | 40% after deductible | |
| Emergency Room Facility Charges | $250 copay for first visit, then 20% after deductible for subsequent visits |
$500 copay for first visit, then 20% after deductible for subsequent visits |
||
| Inpatient Facility Charges | 20% after Deductible | 20% after Deductible | 40% after deductible | |
| Outpatient Facility and Surgical Charges | 20% after deductible | 20% after Deductible | 40% after deductible | |
| Mental Health | ||||
| Inpatient | 20% after deductible | 20% after Deductible | 40% after deductible | |
| Outpatient | $25 copay | $35 copay | 40% after deductible | |
| Substance Abuse | ||||
| Inpatient | 20% after deductible | 20% after deductible | 40% after deductible | |
| Outpatient | $25 copay | $35 copay | 40% after deductible | |
| Other Services | ||||
| Chiropractic | $50 Copay (30 visits combined with other outpatient therapies per plan year) |
$75 Copay (30 visits combined with other outpatient therapies per plan year) |
40% after deductible | |
| Acupuncture | $50 Copay | $75 Copay | 40% after deductible | |